

Last updated: October 20, 2026
Quick Answer: The most effective caregiver home safety and daily living plan usually starts with 4 changes: clear walkways, improve lighting, add bathroom supports, and set up medication and emergency access. Caregiver home safety and daily living — The Complete Guide focuses on those priorities because they address the highest-risk routines first.
Key Takeaways
- The biggest wins are simple fixes: clear paths, steady lighting, safer bathrooms, and fewer rushed decisions.
- Falls often happen at transitions: bathrooms, bedrooms, stairs, entryways, and dim hallways.
- Daily routines are easiest to improve when bathing, toileting, dressing, eating, and medication are each supported one step at a time.
- The first changes should target immediate danger within a day: lighting, trip hazards, bathroom support, and emergency access.
Caregiver home safety and daily living comes down to one thing: making the home easier to move through, safer to use, and simpler to manage without turning it into a hospital. The best setup is often layered—remove obvious hazards, add a few high-value supports, and make daily routines predictable.
I write about aging-in-place, disability access, and home safety planning, so I know the difference between a fix that looks tidy on paper and one that actually helps at 6 a.m. when someone is unsteady, confused, or tired.
What matters most in caregiver home safety?

The biggest wins are simple fixes: clear walking paths, reliable lighting, safer bathrooms, and a routine that reduces rushed decisions. A caregiver does not need a perfect home. A caregiver needs a home that fails less often.
A generic article will tell you to “declutter” and “install grab bars.” That is true, but incomplete. The real issue is friction. Every extra step—searching for glasses, reaching over cords, stepping around a rug, climbing a threshold, opening a stiff medicine bottle—adds risk. The goal is to cut those small failures before they turn into falls, missed doses, burns, or confusion.
A practical rule: start with the rooms used every day, not the rooms that look dangerous. The bedroom, bathroom, kitchen, and the path between them matter more than the attic or guest room. If a caregiver is short on time, the first pass should focus on nighttime trips to the bathroom, getting in and out of bed, bathing, and preparing food safely.
Because those routines happen every day, the first pass should be practical and fast. A good home plan usually starts with the movement path, then the most used touchpoints, then the time-sensitive tasks.
One useful way to think about the home is in three zones:
- Movement: floors, stairs, thresholds, cords, pets, clutter.
- Touch: handholds, faucets, handles, switches, controls.
- Time: medications, meals, sleep, appointments, emergency response.
If those three zones are stable, daily living gets easier fast. If they are not, even a “nice” home can be hard to manage. That is why this guide prioritizes function over appearance.
Where do falls usually happen at home?
Falls usually happen in the transition spots: bathrooms, bedrooms, stairs, entryways, and hallways with poor light or clutter. The fix is not just “be careful.” The fix is to remove the conditions that force balance, speed, or memory to do too much.
Bathrooms are the classic problem because they combine wet floors, turning, sitting, standing, and often low light. A shower chair, non-slip flooring, and grab bars near the toilet and in the shower are more useful than decorative upgrades. A bedside commode can help if the bathroom is too far away or if night walking is unsafe.
According to the CDC, falls are a major older-adult risk, and about 1 in 4 adults age 65 and older falls each year. That makes bathroom changes worth doing early, not after the first incident. For more guidance, see the CDC’s fall-prevention resources and the National Institute on Aging’s home safety advice.
Bedrooms are next. The bed height matters more than many people realize. If a person has to drop too low to sit or push up too far to stand, transfers get harder. A firm mattress edge, a stable chair near the bed, and a clear path to the door reduce strain. A bedside lamp or motion light helps, especially for those who wake at night.
Bedrooms are not only about sleep. They are also where many nighttime falls begin, because the first few steps happen before the person is fully alert.
Stairs deserve respect. If stairs are unavoidable, one handrail is rarely enough when balance is poor. A second rail, brighter lighting, and clear stair edges are safer than hoping for caution. If carrying laundry, water, or groceries makes the stairs feel rushed, the layout is asking for trouble.
The cost of ignoring these zones is not abstract. A small slip can mean a head injury, a broken wrist, a hospital stay, or a sudden loss of confidence that makes the person move less. Less movement often leads to more weakness, which raises the fall risk again. That cycle is why safety changes should happen early, not after the first incident.
A useful check: if the person has to reach, twist, or hurry in the same motion, the home needs adjustment. The National Institute on Aging recommends exactly that kind of practical review in its home-safety guidance.
Which daily routines are easiest to make safer?
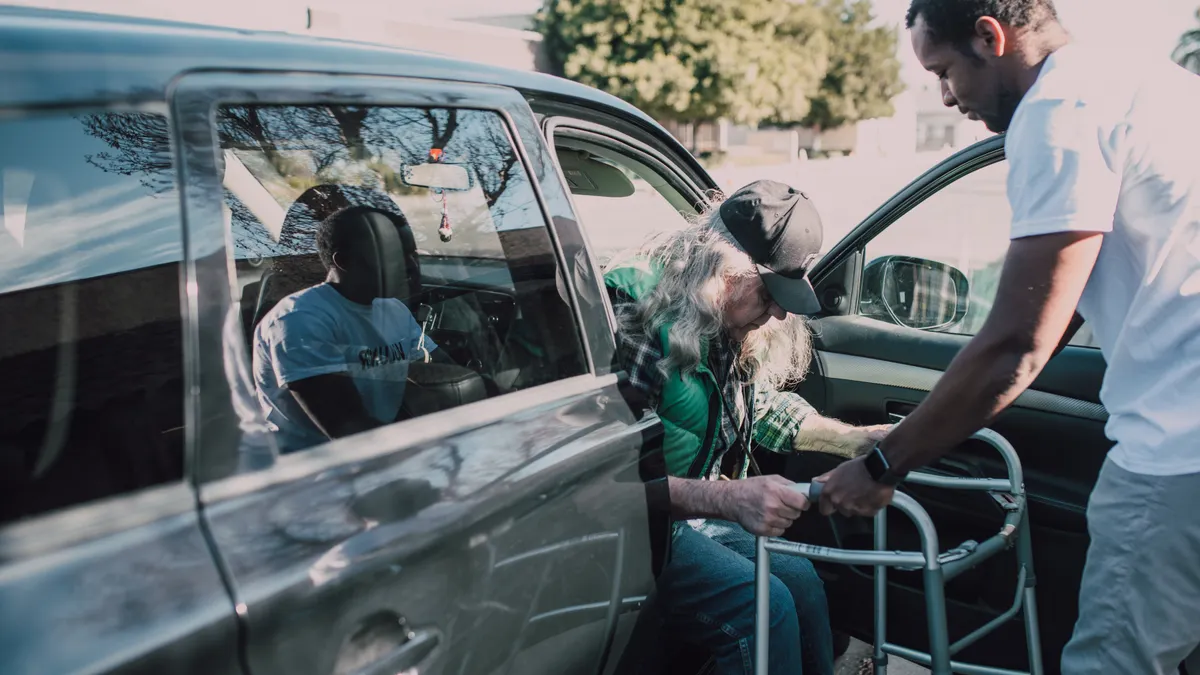
The easiest routines to improve are bathing, toileting, dressing, eating, and medication management because each one can be changed with one or two concrete supports. These are not glamorous fixes, but they reduce the number of decisions the caregiver has to manage every day.
Bathing wins first because it is both private and risky. A handheld shower head, a shower chair, and a non-slip mat can turn a difficult task into one that is slower but safer. The point is not luxury; the point is control. If standing in the shower is shaky, sitting is not a downgrade. It is a risk control.
Toileting is about distance, speed, and access. Clear the route. Keep night lighting on a low setting. Make sure clothing is easy to manage. Raised toilet seats can help when sitting and standing are hard, though they are not for every bathroom because some models wobble or interfere with seating position. If the person uses a walker, the bathroom needs enough space to turn and park it safely.
Dressing gets easier when clothing is chosen for the body that exists now, not the body from ten years ago. Shoes with closed backs and non-slip soles beat loose slippers. Shirts and pants with easy fasteners can save time and frustration. If bending is painful, dressing aids may help, but they should be chosen for simplicity, not novelty.
For clothing and dressing support, the point is not to add gadgets for their own sake. The point is to reduce bending, balancing, and repeated choices.
Eating becomes safer when the kitchen is organized by reach and routine. Daily dishes, cups, and utensils belong at waist height, not on high shelves or in low cabinets. Heavy items should be stored where they can be lifted without crouching. Kettles, pans, and microwaves should be placed to avoid awkward carrying across the room.
Medication management is one of the most overlooked daily-living risks. The issue is not only forgetting doses. It is also double-dosing, mixing pills, or taking the wrong medicine at the wrong time. A pill organizer helps only if the regimen is stable and someone checks it. If prescriptions change often, a blister pack prepared by a pharmacy may be better. For dose changes, dizziness, or confusion, a pharmacist or clinician should review the setup.
A common mistake is trying to fix all routines at once. The better move is to choose the two routines that cause the most strain and make those safe first.
What should a caregiver change first in the home?
The first changes should be the ones that remove immediate danger in under a day: lighting, trip hazards, bathroom support, and emergency access. These are the highest-return fixes because they affect the most routines at once.
Start with the floor. Remove loose rugs, cords across walkways, and small furniture that blocks turning space. If a rug must stay, it should lie flat and stay put. Use cord clips or reroute charging cables so they do not cross traffic paths. Keep pet bowls, footstools, and baskets out of the main route between bed, chair, kitchen, and bathroom.
Next, fix lighting. Hallways, stairs, bedroom paths, and entry doors need light that turns on without searching for a switch. Motion sensors or plug-in night lights are often enough. In a home where a person wakes at night, one well-placed light matters more than a brighter bulb in the wrong room.
Then address bathroom access. If the person is already shaky, it makes sense to move a towel, a toiletry basket, or a commode where it reduces steps. A grab bar installed into wall studs is better than a suction device in places where full body weight may be used. Suction products can be useful as temporary aids, but they are not the same as hardware anchored to the structure.
Emergency access belongs in the first wave too. Post emergency numbers in a visible place. Make sure the phone is charged and easy to reach. Keep keys where the caregiver can grab them quickly. If a home has a smart speaker, medical alert device, or doorbell camera, make sure it is set up before a crisis, not after.
The tough truth is that some homes cannot be made safe enough with small tweaks. If stairs are steep, bathrooms are upstairs only, and the person is becoming more unstable, the plan may need a main-floor living arrangement or a move. That is not failure; it is the point where the home no longer matches the care need.
The National Institute on Aging and the CDC both recommend matching home changes to the person’s actual risk, not to what looks convenient in the moment.
What tools actually help, and which ones are not worth it?
The most useful tools are the ones that solve a repeated problem: falls, transfers, reaching, bathing, or medication timing. Anything that adds setup, maintenance, or confusion is only worth it if the problem is severe enough to justify the extra work.
Grab bars are usually worth it when installed correctly because they provide a stable handhold during high-risk movements. They are most useful near toilets, tubs, and showers. The trade-off is that they need proper mounting. A decorative towel bar is not a grab bar, and a bar that is not anchored into framing may fail when weighted.
Shower chairs help when standing is tiring or unsafe. The drawback is that they take space, must be cleaned, and can make a small tub feel cramped. They are a strong choice for someone who is unsteady, weak, or recovering from illness, but less useful in a huge bathroom where the main problem is not standing but heat intolerance or fatigue.
Raised toilet seats and toilet frames can reduce the effort of sitting and standing. They are helpful when knee pain, hip weakness, or low seat height makes transfers hard. The downside is that some are unstable if the bathroom is small, the floor is uneven, or the user shifts weight abruptly.
Bed rails are tricky. A fixed rail can help with turning and transfers, but a bad setup can create a trap or become a climbing aid for someone who is confused. For a person with dementia or agitation, bedside rails deserve extra caution and professional guidance.
Medication dispensers with alarms can help when timing is the main issue. They are less helpful when the real problem is understanding the regimen or recognizing a missed dose. A device cannot solve a confusing prescription list. It can only remind someone to act on it.
Emergency response devices, including pendants and wrist buttons, are worth considering if the person spends time alone and can reliably wear or activate them. The limitation is obvious: they only help if worn, charged, and understood. A device left in a drawer is a false sense of security.
The tools I would skip first are “cute” convenience gadgets that solve a one-time annoyance but do nothing for safety. If a device does not reduce a real daily hazard, it is noise.
How do you support daily living without taking over?
The best support keeps as much independence as the person can safely handle and steps in only where the task or the timing breaks down. Full takeover too early can create resistance, while too little help can create injury or shame.
This is where many caregivers go wrong. They either hover and do everything, or they keep saying “Try harder” when the person clearly cannot manage a task the old way. The better model is task matching: what can still be done alone, what needs setup, what needs standby help, and what needs direct assistance.
For example, a person may still bathe independently if the shower is modified and the caregiver stays nearby only as backup. Dressing may work with laid-out clothes and shoes already opened. Cooking may still happen if the person handles cold meals while the caregiver handles knives, stovetop heat, or cleanup. That is not a retreat from independence. It is a smarter division of labor.
Routine helps more than improvisation. A visible checklist, a standard time for medication, and a place for keys, glasses, and hearing aids reduce the number of memory tasks the person has to carry. If cognitive decline is present, the routine should be simple enough that it can be repeated on a bad day, not just a good one.
One hard truth belongs here: preserving dignity sometimes means accepting a less attractive solution. A commode in the bedroom may not look elegant, but it can prevent night falls. A dispenser on the counter may not match the decor, but it can prevent missed doses. Safety and style are not equal when the stakes are a broken hip or a hospital admission.
Caregiver support also includes the caregiver’s own body. Lifting without training, twisting during transfers, or moving a person by force can injure both people. If the care task requires more strength than one person can safely provide, that is a signal to get training, equipment, or more help.
When should the whole plan change?
The whole plan should change when the home setup no longer fits the person’s mobility, cognition, or care level. A safer room arrangement is not enough if the daily reality has crossed into repeated falls, wandering, severe weakness, or missed critical care.
The clearest exception scenarios are these:
-
Frequent falls or near-falls keep happening despite basic changes. If lighting, clutter removal, and bathroom support do not reduce the danger, the issue may be gait instability, vision loss, medication side effects, or an environment that no longer works. In that case, consult a clinician or occupational therapist and review the home plan against the person’s current risks.
-
The person cannot reliably use the setup. A device, rail, or dispenser that requires memory, judgment, or fine motor control may fail if dementia, tremor, or delirium is part of the picture.
-
The home structure blocks safety. Steep stairs, narrow bathrooms, missing handrails, poor heating, or no main-floor sleeping area can make the house itself the problem.
-
The caregiver is physically overwhelmed. If transfers, bathing, or toileting need two people or trained handling, the current plan may be unsafe as written. A clinician, home health professional, or occupational therapist can help decide whether the setup is still realistic.
In those cases, the answer may be home health support, a different floor plan, respite care, or a move to a more accessible setting. That is not the same as giving up. It is choosing the level of support that matches the risk.
A practical way to make the decision is to ask one question: can the person get through a normal day and one nighttime emergency without the caregiver having to improvise? If the answer is no, the plan needs more than minor edits.
Home safety changes: the honest side-by-side
The best choice depends on what the home is failing at. Some problems need equipment. Some need layout changes. Some need a higher level of care. The table below shows where each approach wins.
| Criteria | Small home-safety upgrades | Bigger care-and-layout changes | Winner for condition |
|---|---|---|---|
| Up-front disruption | Low; can often be done in a day or weekend | Higher; may require contractors, move planning, or more help | Small upgrades when the person is stable |
| Fall reduction at night | Good if lighting, path clearance, and bedside access are the issue | Better if stairs, distance, or confusion make nights unsafe | Bigger changes when bathroom access is far or stairs are steep |
| Bathing safety | Good with shower chair, grab bars, and non-slip surfaces | Better if the bathroom is too small or transfer help is needed | Bigger changes when transfers are unsafe |
| Medication reliability | Good if the main issue is remembering timing | Better if the regimen is complex or cognition is declining | Bigger changes when dose errors keep happening |
| Caregiver strain | Moderate relief | Larger relief if the setup reduces hands-on transfers | Bigger changes when lifting is becoming unsafe |
| Independence preservation | Often best; keeps the person in familiar space | Can feel like a loss, but may preserve function longer | Small upgrades when independence is still realistic |
| Cost predictability | Usually easier to stage and budget | More variable; may involve bigger commitments | Small upgrades for limited budgets |
| Speed of benefit | Fast | Slower but sometimes more complete | Small upgrades when urgency is high |
| Long-term fit | Limited if the home stays structurally mismatched | Better for progressive mobility or cognition decline | Bigger changes when needs are likely to grow |
The honest conclusion is not that one path is “better” in the abstract. It is that small upgrades are the right first move for a person who is still mostly stable, while larger changes win when the home itself is the barrier. A home that forces unsafe transfers or repeated improvisation needs more than accessories.
The verdict: which home-safety plan to choose and why
Choose small home-safety upgrades if the person is still walking short distances safely, can follow routines, and the biggest risks are clutter, lighting, bathroom access, or medication timing. Choose bigger care-and-layout changes if stairs, repeated falls, dementia, transfer difficulty, or caregiver strain are already making daily life unsafe. Neither if the person needs medical-level supervision, because then the right answer is a clinician-guided care plan, not more household gadgets.
That is the cleanest call. Start with the least disruptive fixes when the problems are local and predictable. Move to layout changes or more help when the risks are repeated, structural, or cognitive.
What a strong caregiver plan should include on day one
A strong caregiver plan should include a safe route, a bathroom strategy, a medication system, and one emergency backup plan. Those four items matter more than any decorative or convenience upgrade.
A simple day-one checklist looks like this:
- Clear walkways from bed to bathroom and kitchen.
- Add night lighting in hallways and by the bed.
- Put daily items within easy reach.
- Install or confirm stable bathroom supports.
- Organize medications in one visible, labeled place.
- Keep emergency contacts accessible.
- Decide who helps if the caregiver is unavailable for a few hours.
If the person has diabetes, heart failure, Parkinson’s disease, dementia, recent surgery, or another condition that changes balance, thinking, or energy, a clinician or occupational therapist should be part of the planning. That is not overkill. It is a way to match the home to the actual risks. For more evidence-based guidance, consult the CDC, the National Institute on Aging, and an occupational therapy professional when the situation is changing quickly.
The best caregiver homes are not the fanciest ones. They are the ones where the person can move, wash, eat, and rest with the fewest chances for avoidable harm. That goal is plain, but it takes discipline to build.
Drafted with AI; not yet reviewed by a person.


